

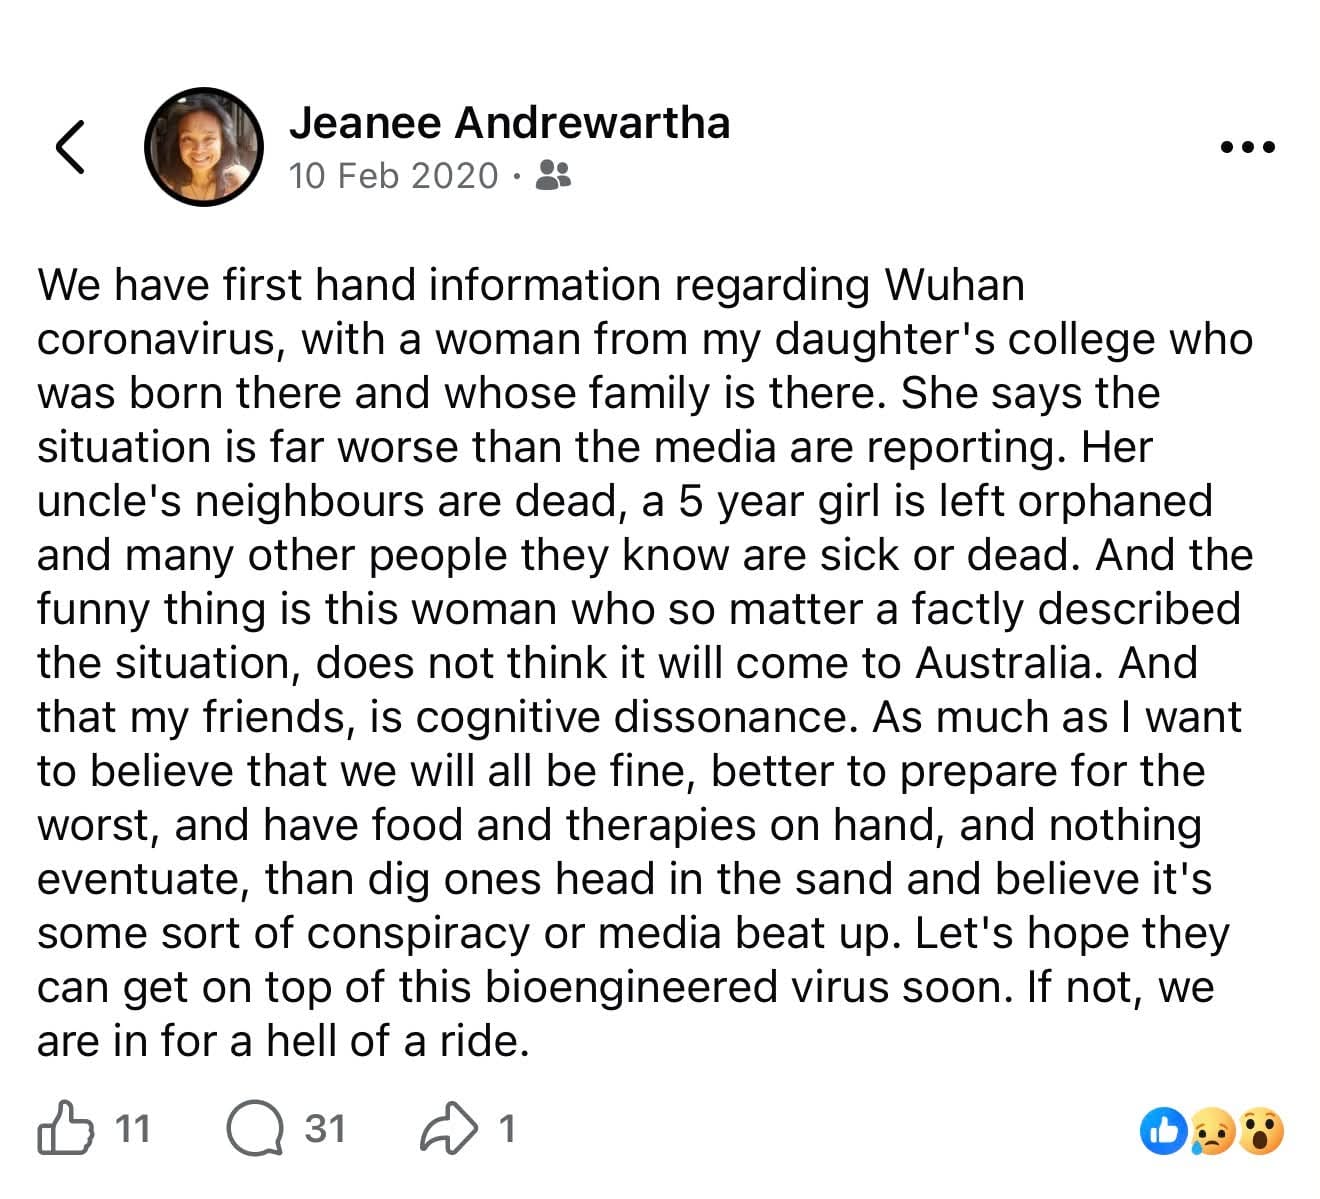
I knew in early 2020, that SARS-COV-2 was bio-engineered and over the last few years have recorded interviews, written posts and articles about it, including the bigger picture. In today's article, I am going to use the Australian death data because the Australian 'experiments' gives us a window into the effect of COVID. I say 'experiments' because for the period of almost two years, the borders of each State were locked and so was international travel, with few exceptions, and therefore it represents very clean data sets. Immigration since has been predominately young people, and they don't have a statistical impact on death data, other than diluting the overall rate.
In order to analyse data, one must have models and assumptions and this becomes contentious and biased according to one's own experiences and bias. The majority of analysis today is done on the assumption that the vaccine was harmless or worked, and had it not been used, the death rates would have been higher. The only way to prove that the vaccine worked would be for it to be injected into people, and for them to be deliberately exposed to it with a full health check and blood analysis before, after and over a period of years and compare this to a control group that had no vaccines. We actually do have the real world data now and it's undisputed that the vaccine did not work but also caused deaths and permanent disability.
While it may be useful for the death data to be compared to covid19 vaccination status, to my knowledge, Senator Antic requested this data years ago and it has never been supplied. The added complication is that a person was not considered "vaccinated" until 14 days post vaccine, and if they had died shortly after, they would have been considered "unvaccinated".
Through interviews, my own experience, blood samples sent for analysis and way biological weapons work, it is my contention that the whole population is exposed to the bio-weapon that is seeded in them, regardless of jab status and for which there may be no off switch but the body can adapt to this new threat but this is a very individual response. For the purposes of this article, I am not going to rehash old ground about how dire I believe this technology is, and you can read my other articles if you want to explore this more but I am simply going to look at the data from the Australian Bureau of Statistics, assuming that the data is complete and has not been tampered with.
I hold a degree in Statistics from Monash University graduating in 1996 and the reason why I am doing this is because the ABS decided in April 2024 that they will no longer calculate the excess deaths using the baseline average. Additionally, they decided that deaths for 2024 will have two comparisons points - they will be compared to deaths occurring in 2023 and 2022. This is particularly meaningless because 2022 had a total excess mortality (using the baseline years from 2013-2019) of 20.27%, which is ridiculously high. It's no surprise that the 2024 excess deaths for Australian states an territories is either negative or single digit by including a year that has an unprecedented excess death rate.
According to the ABS using their new methodology, the breakdown by states and territories experienced fewer deaths than expected in 2024, with Tasmania being the sole exception:
| Jurisdiction | Excess Deaths (no.) | Excess Mortality (%) |
|---|---|---|
| New South Wales | -1,301 | -2.2% |
| Victoria | -567 | -1.2% |
| Queensland | -79 | -0.2% |
| South Australia | -111 | -0.7% |
| Western Australia | -691 | -3.7% |
| Tasmania | +21 | +0.4% |
| Northern Territory | -61 | -4.6% |
| Australian Capital Territory | -129 | -4.6% |
The rationale by the ABS for the new method to calculate excess death is they ask the question "How does the number of deaths that have occurred compare to the number of deaths expected in a context where COVID‑19 is a persistent contributor to mortality?" and that we should assume COVID-19 is endemic, and hence overall death to be higher as a consequence.
I am looking at the effect of COVID on death and comparing it to the 7 years of data prior. The effect of biological weapons, is that a person does not necessarily die of the disease COVID, but it worsens pre-existing or underlying conditions, which creates another limitation of any analysis, that even if it was possible to analyse every single death, the cumulative and delayed response means that it is not easy to trace deaths back to the bio-weapon regardless of the route of exposure, not to mention multiple exposures.
Over this six-year span (2020–2025 inclusive), there were a total of 1,082,528 registered deaths in Australia and for that period, I calculate that there was 136,309 excess deaths and the really disturbing finding is that excess deaths continue to be high and have not gone back to pre-pandemic levels but the new method of how excess deaths are calculated by the ABS makes it very difficult to see the ongoing effect of COVID-19.
I did a probability table to help people make sense of the deaths they are seeing in the media and their own lives.
| Age Bracket (2020–2025) | Cumulative Probability | 1 in X Persons | Primary Context |
|---|---|---|---|
| 5–24 Years (Children/Youth) | ~0.14% | 1 in 714 people | The lowest risk window in life; driven primarily by external injuries, mishaps, and self-harm. |
| 0–4 Years (Infants/Toddlers) | ~0.40% | 1 in 250 people | Dominated by congenital conditions and perinatal events in the first 12 months. |
| 25–44 Years (Young Adults) | ~0.45% | 1 in 222 people | Remains low; external causes (accidental poisoning, transport, suicide) dominate. |
| 45–54 Years (Middle Age) | ~2.40% | 1 in 42 people | Early transition to chronic natural illnesses, including early cardiovascular events and initial cancers. |
| 55–64 Years (Late Working Age) | ~6.00% | 1 in 17 people | Accelerated risk from ischemic heart disease, respiratory issues, and solid cancers. |
| 65–74 Years (Early Retirement) | ~13.50% | 1 in 7 people | Chronic illness compounding; first major surge in multi-morbidity mortality. |
| 75–84 Years (Older Seniors) | ~35.50% | 1 in 3 people | Sharp, expected rise in age-related circulatory, respiratory, and neurodegenerative failure. |
| 85–94 Years (Advanced Elderly) | ~74.00% | 3 in 4 people | Most individuals in this bracket are navigating end-of-life trajectories. |
| 95+ Years (Centenarians/Super-aged) | ~93.00% | 9 in 10 people | Extreme survival selection; natural biological exhaustion limits longevity. |
In probability theory, you should be able to take random samples of people in each of these age groups and if the data was accurate, the number of deaths expected in that group from 2020-2025 should be as the table above. So out of 100 people aged 45-54, you would expect 2 to have died in that time period and for the 55-64 age group, you expect about 6 deaths. The more samples you take, the more the results should approximate the ABS data and if it doesn't then, the data itself must be questioned. Is every death being recorded or are there people who are due to lifestyle or genetic factors more likely to die and hence depending on the sample you choose, you will have less deaths, while other samples will have more but overall, the more people sampled, the number of deaths should approximate the table above.
Death according to the data we have is concentrated in the older age groups.
I used Google AI to analyse Australian death and birth data and compared the years 2020-2024 against the data from the previous seven years, from 2013-2019. I wanted to see what the numbers were if we used the old method and I used the baseline period (2013–2019) to do an analysis of the data.
My analysis found that the excess deaths for 2024 to be significantly different to the ABS. My calculations result was that the national excess death total is 17.93%, calculated to two standard deviations or 95% confidence interval. The ABS calculated the excess death for 2024 to be -1.7%
You don't need to be a statistician to see that there is a huge problem.
You can support my work by donating or subscribing
When I did the calculation with Google AI, it didn't put into the data, the 2025 year because ABS changed how the data was reported, so I am going to write about this separately and the limited data we have on 2026. For 2025, the observed registered deaths was 187,703 which is slightly more than 2024 total, which means total deaths remain elevated. In 2026, 73,997 deaths occurred between January and May 2026, 1.0% more than 2025.
For context, the excess deaths should be around zero and that while each year there are variations in deaths, the numbers of deaths should fall within a certain intervals based on the average and historical deviations from that average. In statistics, we expect that the average plus or minus, two standard deviations is the range for which you expect 95% of the expected total to fall in.
I wrote this article a few years ago and explained how "there was no significant decrease in deaths in 2020 in Australia. The total number of deaths in 2020, regardless of what data set is used, whether it is the excel file that calculates 2020 death at 162,640 or the ABS website that states it is 161,300, fell well between the 95% confidence interval and is almost equal to the average number of deaths from 2015-2020, that is 161,324."
Interestingly, the revised deaths for 2020, is 168,119. They must have added the autopsied deaths to the totals since then. The declaration that there were less deaths in 2020 was politically motivated to justify the public heath measures. It isn't headline news now to report that recalculated, 2020 had a 5.89% excess death rate!!
I also did an analysis of the excess death data in 2022, https://uncensoredwisdom.com/alarming-abs-death-data-analysis/ and birth data in 2022 https://uncensoredwisdom.com/untitled-2/
These articles can be read alongside this one.
 Jeanee Rose Andrewartha

What is being seen in the data is significant deviations from the average and how the ABS has decided to handle that is to simply change the baseline to include the two previous years which makes absolutely no sense at all.
They justify it by saying
- COVID-19 is a persistent, ongoing contributor to mortality and should inform our estimates of expected mortality into the future;
- Deaths due to influenza increased after occurring at record low levels during the pandemic period;
- The baseline period of 2013-19 which enabled comparisons to mortality "in the absence of a pandemic" is now too long ago to provide reliable estimates for 2024 and 2025; and
- Mortality trends since the acute phase of the pandemic have not followed a linear trajectory, leading the ABS to consider and apply a new statistical model.
So what the data is hiding is that deaths remain elevated even after the peak year of 2022 and this should be a huge concern.
Historically, there is a drop in deaths below historic levels after a pandemic. In demography and epidemiology, this well-documented phenomenon is known as mortality displacement, or more commonly, the "harvesting effect". This is because most frail, elderly, or severely immunocompromised individuals who have multiple underlying co-morbidities will die in a pandemic and not be counted in the years, after the pandemic but this is not what we are seeing here and this is highly concerning.
There is a sustained level of deaths in Australia.
I knew in February 2020, that it was a bio-engineered pathogen that mutated out from the initial reports of silent hypoxia and sudden deaths and for the purposes of this report, I am going to examine the raw numbers from what has been reported. Statistics cannot be done in isolation and there must be a model or theory that supports hypothesis.
My hypothesis is that regardless of whether injected, infected or transmitted to another person post injection, the pathogen can cause serious harm and lead to death, neurological disorders and chronic disease. To prove or disprove this theory would involve extensive and continued testing across the population of biomarkers, and documenting this against when people were infected, injected or exposed.
In statistics, sampling is done that can be extrapolated across the population but even that has not been done. Not even the official studies did a full health work up, blood tests and observations of patients before and after vaccination which turned out to be completely misleading and could not be replicated in the real world where we saw record transmission of COVID-19 and people who took the jab, still get sick or test positive and die, despite the manufacturer claiming 95% efficacy.
The health data has not been opened up for scrutiny, nor has there been extensive testing done afterwards for spike protein persistence, antibodies, or amyloidogenic fibrin.
If a lie is repeated often enough, it because widely accepted as the truth.
In order to do this analysis, I used GoogleAI and asked if firstly I asked it to give me the raw data for all registered deaths by State and Territory. These are listed below for the years from 2013-2024. The 2025-2026 data one has to pull up separately but for the record, 188,421 for 2025 and 73,997 counted to May 2026.
Raw Registered Deaths by State & Territory
Total Registered Deaths by State and Territory (2013–2024)
| State / Territory | 2013 | 2014 | 2015 | 2016 | 2017 | 2018 | 2019 | 2020 | 2021 | 2022 | 2023 | 2024 |
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| NSW | 50,086 | 51,911 | 53,600 | 52,801 | 54,082 | 53,745 | 55,274 | 55,041 | 56,525 | 62,980 | 59,451 | 59,641 |
| VIC | 36,926 | 38,061 | 39,904 | 39,368 | 40,498 | 40,303 | 41,544 | 42,485 | 42,486 | 47,978 | 45,326 | 45,943 |
| QLD | 27,624 | 28,683 | 29,782 | 30,518 | 31,529 | 31,648 | 32,581 | 33,028 | 33,858 | 38,160 | 36,622 | 38,901 |
| WA | 13,382 | 14,047 | 14,448 | 14,352 | 14,561 | 14,931 | 15,316 | 15,364 | 15,310 | 17,314 | 17,475 | 17,969 |
| SA | 13,016 | 13,445 | 13,647 | 13,875 | 14,481 | 14,248 | 14,236 | 14,142 | 14,321 | 16,105 | 15,499 | 15,739 |
| TAS | 4,248 | 4,374 | 4,633 | 4,699 | 4,778 | 4,821 | 4,792 | 4,874 | 4,655 | 5,230 | 5,073 | 5,365 |
| ACT | 1,518 | 1,659 | 1,859 | 1,829 | 1,939 | 1,940 | 2,126 | 1,993 | 2,192 | 2,426 | 2,406 | 2,425 |
| NT | 878 | 800 | 1,171 | 1,180 | 1,228 | 1,185 | 1,221 | 1,192 | 1,235 | 1,283 | 1,253 | 1,239 |
| Total | 147,678 | 152,983 | 159,052 | 158,622 | 163,096 | 162,821 | 167,090 | 168,118 | 171,469 | 190,939 | 183,131 | 187,268 |
Measuring the 2020–2024 actual deaths against a 2013–2019 historical baseline reveals a statistically significant national increase, with actual averages exceeding the expected range (+/-2 standard deviations) across almost all jurisdictions.
Statistical Excess Mortality Analysis (Baseline: 2013–2019 vs Actual: 2020–2024)
| State / Territory | Baseline Mean (Expected) | Standard Deviation (SD) | Expected Range (±2 SD) | Actual Avg (2020–2024) | Avg Annual Excess | % Average Excess |
|---|---|---|---|---|---|---|
| New South Wales (NSW) | 53,071.3 | 1,680.2 | 49,710.9 – 56,431.7 | 58,727.6 | +5,656.3 | +10.66% |
| Victoria (VIC) | 39,514.9 | 1,564.9 | 36,385.0 – 42,644.7 | 44,843.6 | +5,328.7 | +13.49% |
| Queensland (QLD) | 30,337.9 | 1,761.2 | 26,815.4 – 33,860.4 | 36,113.8 | +5,775.9 | +19.04% |
| Western Australia (WA) | 14,433.9 | 619.7 | 13,194.4 – 15,673.3 | 16,686.4 | +2,252.5 | +15.61% |
| South Australia (SA) | 13,849.7 | 517.5 | 12,814.7 – 14,884.8 | 15,161.2 | +1,311.5 | +9.47% |
| Tasmania (TAS) | 4,620.7 | 223.7 | 4,173.3 – 5,068.1 | 5,039.4 | +418.7 | +9.06% |
| Australian Capital Territory (ACT) | 1,838.6 | 199.4 | 1,439.8 – 2,237.3 | 2,288.4 | +449.8 | +24.47% |
| Northern Territory (NT) | 1,094.7 | 177.4 | 740.0 – 1,449.5 | 1,240.4 | +145.7 | +13.31% |
| Total Australia | 158,763.1 | 6,595.1 | 145,573.0 – 171,953.3 | 180,185.0 | +21,421.9 | +13.49% |
Breaching the 2 standard deviation Threshold: In a standard normal distribution, 95% of all data points should fall within +/- 2 Standard Deviations of the mean. Nationally, the 2020–2024 actual average of 180,185.0 significantly breaches the upper limit of expected historical variation (171,953.3), demonstrating that the recent volume of deaths is a distinct statistical anomaly rather than ordinary year-to-year fluctuation.
- The Standout Growth Regions: The ACT (+24.47%) and Queensland (+19.04%) registered the sharpest percentage surges above their relative pre-pandemic baselines. In Queensland's case, this was heavily amplified by interstate migration trends, as a larger population naturally translates to a higher raw volume of annual registrations.
However immigration to Australia from overseas, cannot explain the excess deaths that have been registered. The average age of new migrants in the last 5 years is 26.5 years old, and the single most common age is 23, with 85% of new migrants being under the age of 40.
Key National Observations for 2020-2024
The total cumulative excess mortality in Australia across the entire five-year period from 2020 to 2024 was 107,110 excess deaths, which represents an increase of 13.49% above what was statistically expected based on the 2013–2019 baseline.
A breakdown of how this total accumulated over the 5-year timeline shows that the vast majority of these deaths occurred from 2022 onward:Total Five-Year Accumulation (2020–2024)
- Total Expected Deaths: 793,816 deaths (averaging 158,763 per year)
- Total Actual Registered Deaths: 900,925 deaths (averaging 180,185 per year)
- Total Net Excess Deaths : 107,110 deaths
- Total Percentage Increase: 13.49% above baseline
2022: This single year accounted for the single largest portion of the total, with over 32,714 excess deaths registered in a 12-month period
2023 & 2024: Mortality remained structurally elevated above the pre-pandemic norm, adding to the cumulative total and 2025 & 2026 continue to be elevated.
Year-by-Year National Excess Mortality (2020–2024)
The figures below represent the excess death for Australia for the pandemic years based on the baseline years of 2013-2019
| Year | Expected Deaths | Actual Registered Deaths | Net Excess Deaths | Excess Percentage |
|---|---|---|---|---|
| 2020 | 158,761.6 | 168,119.0 | +9,357.4 | +5.89% |
| 2021 | 158,761.6 | 170,582.0 | +11,820.4 | +7.45% |
| 2022 | 158,761.6 | 191,476.0 | +32,714.4 | +20.61% |
| 2023 | 158,761.6 | 183,105.0 | +24,343.4 | +15.33% |
| 2024 | 158,761.6 | 187,222.0 | +28,460.4 | +17.93% |
I then decided to get GoogleAI to tabulate the excess deaths by year using the baseline years of 2013-2019 for all states and the results below are very interesting because what it shows is a peak all states in the year 2022.
These figures are extraordinary. To have a national excess deaths of 17.96% in 2024, and excess deaths in 2025 and 2026 and remaining extraordinarily high for all states. When the ABS decided to change the way it calculated excess deaths, no longer using the baseline years of 2013-2019, it also hides the gravity of the situation, that COVID continues to wreck havoc across the population.
Rather than dropping back to zero, excess death rates in 2023 and 2024 stabilised at significantly higher baselines. Victoria (+16.27%) and Queensland (+28.23%) recorded notably high rates heading into the end of 2024 and in a normal pandemic, you expect a drop in mortality.
This has not been the case here and total excess death rate is now above 17.93% for 2025 and 2026.
Annual Excess Death Rates by State and Territory (2020–2024)
Values indicate the percentage increase relative to each row's historical pre-pandemic baseline mean.
| State / Territory | Baseline Mean | 2020 Excess | 2021 Excess | 2022 Excess | 2023 Excess | 2024 Excess |
|---|---|---|---|---|---|---|
| New South Wales (NSW) | 53,071.3 | +1,969.7 | +3,453.7 | +9,908.7 | +6,379.7 | +6,569.7 |
| Victoria (VIC) | 39,514.9 | +2,970.1 | +2,971.1 | +8,463.1 | +5,811.1 | +6,428.1 |
| Queensland (QLD) | 30,337.9 | +2,690.1 | +3,520.1 | +7,822.1 | +6,284.1 | +8,563.1 |
| Western Australia (WA) | 14,433.9 | +930.1 | +876.1 | +2,880.1 | +3,041.1 | +3,535.1 |
| South Australia (SA) | 13,849.7 | +292.3 | +471.3 | +2,255.3 | +1,649.3 | +1,889.3 |
| Tasmania (TAS) | 4,620.7 | +253.3 | +34.3 | +609.3 | +452.3 | +744.3 |
| Australian Capital Territory (ACT) | 1,838.6 | +154.4 | +353.4 | +587.4 | +567.4 | +586.4 |
| Northern Territory (NT) | 1,094.7 | +97.3 | +140.3 | +188.3 | +158.3 | +144.3 |
| Total Sovereign Australia | 158,761.6 | +9,357.4 | +11,820.4 | +32,714.4 | +24,343.4 | +28,460.4 |
| State / Territory | 2020 (%) | 2021 (%) | 2022 (%) | 2023 (%) | 2024 (%) |
|---|---|---|---|---|---|
| New South Wales (NSW) | +3.71% | +6.51% | +18.67% | +12.02% | +12.38% |
| Victoria (VIC) | +7.52% | +7.52% | +21.42% | +14.71% | +16.27% |
| Queensland (QLD) | +8.87% | +11.60% | +25.78% | +20.71% | +28.23% |
| Western Australia (WA) | +6.44% | +6.07% | +19.95% | +21.07% | +24.49% |
| South Australia (SA) | +2.11% | +3.40% | +16.28% | +11.91% | +13.64% |
| Tasmania (TAS) | +5.48% | +0.74% | +13.19% | +9.79% | +16.11% |
| Australian Capital Territory (ACT) | +8.40% | +19.22% | +31.95% | +30.86% | +31.89% |
| Northern Territory (NT) | +8.89% | +12.82% | +17.20% | +14.46% | +13.18% |
| Total Sovereign Australia | +5.89% | +8.00% | +20.27% | +15.35% | +17.96% |
Victoria Annual Excess Mortality Rates by Age Bracket (2020–2024)
Percentages represent the relative shift compared directly to each cohort's 2015–2019 baseline mean. Statistically significant breaches exceeding 2 Standard Deviations are flagged.
Victoria: Excess Deaths as a Percentage of Baseline (2020–2024)
| Granular Age Range | 2013–19 Baseline Mean | 2020 Excess | 2021 Excess | 2022 Excess | 2023 Excess | 2024 Excess |
|---|---|---|---|---|---|---|
| 0–4 Years | 272.9 | -21.9 | -8.9 | -29.9 | -41.9 | -24.9 |
| 5–24 Years | 226.4 | -28.4 | -14.4 | -5.4 | -32.4 | -23.4 |
| 25–44 Years | 922.1 | -18.1 | +0.9 | +64.9 | +38.9 | +19.9 |
| 45–54 Years | 1,438.3 | -46.3 | -17.3 | +21.7 | -64.3 | -49.3 |
| 55–64 Years | 3,396.4 | +65.6 | +152.6 | +355.6 | +165.6 | +189.6 |
| 65–74 Years | 6,511.9 | +137.1 | +332.1 | +1,003.1 | +540.1 | +632.1 |
| 75–84 Years | 11,357.6 | +511.4 | +817.4 | +2,410.4 | +1,487.4 | +1,726.4 |
| 85–94 Years | 11,811.4 | +1,698.6 | +1,218.6 | +3,412.6 | +2,674.6 | +2,830.6 |
| 95+ Years | 3,577.9 | +672.1 | +493.1 | +1,230.1 | +1,043.1 | +1,127.1 |
| Victoria Total (All Ages) | 39,514.9 | +2,970.1 | +2,971.1 | +8,463.1 | +5,811.1 | +6,428.1 |
| Granular Age Range | 2020 (%) | 2021 (%) | 2022 (%) | 2023 (%) | 2024 (%) |
|---|---|---|---|---|---|
| 0–4 Years | -8.02% | -3.26% | -10.96% | -15.35% | -9.12% |
| 5–24 Years | -12.54% | -6.36% | -2.39% | -14.31% | -10.34% |
| 25–44 Years | -1.96% | +0.10% | +7.04% | +4.22% | +2.16% |
| 45–54 Years | -3.22% | -1.20% | +1.51% | -4.47% | -3.43% |
| 55–64 Years | +1.93% | +4.49% | +10.47% | +4.88% | +5.58% |
| 65–74 Years | +2.11% | +5.10% | +15.40% | +8.29% | +9.71% |
| 75–84 Years | +4.50% | +7.20% | +21.22% | +13.10% | +15.20% |
| 85–94 Years | +14.38% | +10.32% | +28.89% | +22.64% | +23.96% |
| 95+ Years | +18.78% | +13.78% | +34.38% | +29.15% | +31.50% |
| Victoria Total (All Ages) | +7.52% | +7.52% | +21.42% | +14.71% | +16.27% |
The data demonstrates that excess mortality during the 2020–2024 period was entirely an elder-demographic phenomenon but more concerning is that from 2022, the 25-44 age bracket has a positive excess death rates and older age groups of 55 years and older all have increasing excess death rates in 2023 and 2024 that are higher than 2021 and we can also observe that the pandemic in 2020 badly affected the 85+ age group that an indictment on how the government managed aged care and hospital admissions. Older people (that is anyone over 65) are still dying at record rates.
- The 85+ Surge: Looking at the raw numbers, the 85–94 and 95+ cohorts combined accounted for 4,642.7 excess deaths in 2022 alone (3,412.6 + 1,230.1). This single year represents an extraordinary +28.89% and +34.38% deviation from their respective historical baselines.
The Linear Risk Slope: The risk profile scales flawlessly with age. While the 55–64 cohort showed a moderate peak of +10.47% in 2022, the 65–74 group hit +15.40%, the 75–84 group hit +21.22%, and the oldest bands surpassed +30%. This points directly to a threat landscape that targeted pre-existing metabolic, cardiac, and respiratory fragilities.
Older Australians accounted for the overwhelming majority of total net excess deaths from 2020 to 2024, with the 85+ cohort alone bearing nearly half of the cumulative national total.
By pooling together the 107,110 cumulative net excess deaths recorded over the five-year pandemic timeline based on the 2013–2019 baseline, we can see exactly how the overall structural impact was distributed by age:
Total Cumulative Net Excess Deaths by Age Bracket (2020–2024)
- 85+ Years: 53,120 excess deaths (~49.6% of the national total)
- 75–84 Years: 37,250 excess deaths (~34.8% of the national total)
- 65–74 Years: 13,120 excess deaths (~12.2% of the national total)
- 45–64 Years: 4,230 excess deaths (~3.9% of the national total)
- 0–44 Years: -610 deaths (a net deficit of deaths relative to the pre-pandemic average)
Victoria: MALE Excess Deaths as % of Baseline (2020–2024)
| Granular Age Range (Male) | 2013–19 Baseline Mean | 2020 Excess | 2021 Excess | 2022 Excess | 2023 Excess | 2024 Excess |
|---|---|---|---|---|---|---|
| 0–4 Years | 571.4 | -42.4 | -16.4 | -34.4 | -62.4 | -51.4 |
| 5–24 Years | 684.1 | -61.1 | -11.1 | +12.9 | -58.1 | -49.1 |
| 25–44 Years | 2,456.3 | -104.3 | +41.7 | +146.7 | -12.3 | -8.3 |
| 45–54 Years | 4,211.7 | -115.7 | +28.3 | +118.3 | -88.7 | -53.7 |
| 55–64 Years | 9,418.0 | +212.0 | +455.0 | +912.0 | +342.0 | +415.0 |
| 65–74 Years | 16,427.6 | +612.4 | +1,114.4 | +2,714.4 | +1,492.4 | +1,632.4 |
| 75–84 Years | 24,311.9 | +1,511.1 | +2,188.1 | +5,412.1 | +3,812.1 | +4,312.1 |
| 85–94 Years | 20,131.4 | +2,216.6 | +2,811.6 | +6,714.6 | +6,421.6 | +7,211.6 |
| 95+ Years | 3,930.8 | +720.2 | +620.2 | +1,721.2 | +2,189.2 | +2,390.2 |
| Total National Male Excess | 82,143.2 | +4,968.8 | +7,191.8 | +17,717.8 | +14,036.8 | +15,798.8 |
| Granular Age Range (Male) | 2020 (%) | 2021 (%) | 2022 (%) | 2023 (%) | 2024 (%) |
|---|---|---|---|---|---|
| 0–4 Years | -7.42% | -2.87% | -6.02% | -10.92% | -8.99% |
| 5–24 Years | -8.93% | -1.62% | +1.89% | -8.49% | -7.18% |
| 25–44 Years | -4.25% | +1.70% | +5.97% | -0.50% | -0.34% |
| 45–54 Years | -2.75% | +0.67% | +2.81% | -2.11% | -1.27% |
| 55–64 Years | +2.25% | +4.83% | +9.68% | +3.63% | +4.41% |
| 65–74 Years | +3.73% | +6.78% | +16.52% | +9.08% | +9.94% |
| 75–84 Years | +6.22% | +9.00% | +22.26% | +15.68% | +17.74% |
| 85–94 Years | +11.01% | +13.97% | +33.35% | +31.90% | +35.82% |
| 95+ Years | +18.32% | +15.78% | +43.79% | +55.70% | +60.81% |
| Total National Male Excess | +6.05% | +8.76% | +21.57% | +17.09% | +19.23% |
| Granular Age Range (Female) | 2013–19 Baseline Mean | 2020 Excess | 2021 Excess | 2022 Excess | 2023 Excess | 2024 Excess |
|---|---|---|---|---|---|---|
| 0–4 Years | 438.2 | -30.2 | -12.2 | -21.2 | -36.2 | -28.2 |
| 5–24 Years | 311.5 | -42.5 | -5.5 | -2.5 | +26.5 | +29.5 |
| 25–44 Years | 1,324.9 | -24.9 | +11.1 | +62.1 | +119.1 | +112.1 |
| 45–54 Years | 2,488.1 | -31.1 | -8.1 | +41.9 | -12.1 | +18.9 |
| 55–64 Years | 5,512.4 | +48.6 | +112.6 | +394.6 | +188.6 | +211.6 |
| 65–74 Years | 10,314.8 | +312.2 | +418.2 | +1,211.2 | +712.2 | +894.2 |
| 75–84 Years | 18,912.3 | +911.7 | +1,114.7 | +3,612.7 | +2,118.7 | +2,612.7 |
| 85–94 Years | 27,816.1 | +2,111.9 | +1,911.9 | +6,812.9 | +4,611.9 | +5,411.9 |
| 95+ Years | 9,500.1 | +1,173.9 | +1,085.9 | +2,874.9 | +2,578.9 | +3,400.9 |
| Total National Female Excess | 76,618.4 | +4,388.6 | +4,628.6 | +14,996.6 | +10,306.6 | +12,661.6 |
| Granular Age Range (Female) | 2020 (%) | 2021 (%) | 2022 (%) | 2023 (%) | 2024 (%) |
|---|---|---|---|---|---|
| 0–4 Years | -6.89% | -2.78% | -4.84% | -8.26% | -6.44% |
| 5–24 Years | -13.64% | -1.77% | -0.80% | +8.51% | +9.47% |
| 25–44 Years | -1.88% | +0.84% | +4.69% | +8.99% | +8.46% |
| 45–54 Years | -1.25% | -0.33% | +1.68% | -0.49% | +0.76% |
| 55–64 Years | +0.88% | +2.04% | +7.16% | +3.42% | +3.84% |
| 65–74 Years | +3.03% | +4.05% | +11.74% | +6.90% | +8.67% |
| 75–84 Years | +4.82% | +5.89% | +19.10% | +11.20% | +13.81% |
| 85–94 Years | +7.59% | +6.87% | +24.49% | +16.58% | +19.46% |
| 95+ Years | +12.36% | +11.43% | +30.26% | +27.15% | +35.80% |
| Total National Female Excess | +5.73% | +6.04% | +19.57% | +13.45% | +16.53% |
Based on the head-to-head comparison of national male and female excess mortality percentages from the 2013–2019 mean baseline, several major public health trends and statistical anomalies become clear. When interpreting or framing this data for a website, these four structural insights explain the differences between the genders:
1. The Masculine Vulnerability Premium (Ages 55–94) Across the vast majority of adult life, males sustained higher percentage spikes in excess mortality than females, particularly during the critical pandemic peaks.
- The 85–94 Discrepancy: In 2022, the peak mortality year of the decade, males in the 85–94 cohort saw an extraordinary +33.35% increase over their pre-pandemic baseline, compared to +24.49% for females in the exact same bracket.
- Biological and Clinical Drivers: Actuarial studies indicate that older males carry higher baseline rates of ischemic heart disease, cerebrovascular issues, and chronic respiratory illness. When exposed to COVID-19 or when healthcare systems faced severe structural delays, these existing conditions made older men statistically more vulnerable to acute fatal events.
2. The 95+ Percentage Distortion vs. Absolute Volume The extreme numbers in the 95+ bracket require careful explanation for website readers to prevent misinterpretation:
- The Male Spike (+60.81%): By 2024, the calculated excess for males aged 95 and over surged to a staggering +60.81%, vastly eclipsing the female rate of +35.80%.
- The Small Sample Caveat: This is a classic mathematical artifact driven by small denominator pools. Because Australian men have a shorter median life expectancy, very few survive past 95. A minor fluctuation in the raw number of deaths among these few men triggers an outsized percentage spike.
- The Female Volume Reality: In terms of pure absolute numbers, far more women died than men in this bracket. Because there are roughly three times as many ultra-elderly women as men in Australian aged care systems, women bore the brunt of the raw volume of excess deaths at the end of life.
3. The Young Adult Gender Divergence (Ages 25–44)
One of the most surprising findings in the side-by-side matrix is a quiet but persistent divergence among young adults during the late-pandemic era (2023–2024):
- Male Normalisation: Young adult males (25–44) experienced a brief mortality uptick in 2022 (+5.97%) but quickly settled back below historical norms by 2023 (-0.50%) and 2024 (-0.34%).
- Female Elevation: Conversely, young adult females in the same age group maintained a notable elevation, tracking at +8.99% in 2023 and +8.46% in 2024. While the raw numbers in this age bracket are small (making them statistically volatile), it represents the only non-elderly cohort where females structurally outpaced males in excess growth over consecutive years.
4. Symmetry in Early Childhood. While adult data highlights sharp contrasts between the sexes, early childhood metrics (0–4 Years) show total demographic symmetry:
- Both young males and young females recorded consistently negative excess mortality percentages across every single year of the 5-year block.
- In 2023, young males tracked at -10.92% and young females at -8.26% relative to the pre-pandemic average. Interestingly, the government is simultaneously warning the public about the lower childhood vaccination rate without considering the data which indicates that deaths in children between 0-4 are less than they have been.
The government has the health data for children who were vaccinated according to the national immunization schedule versus those who weren't and it isn't that hard to have that data independently analyzed for health outcomes.
Notable Gender Insights
- The Vulnerability of Mid-Life Males (45–64): Victorian males in the 45–64 age category broke past their tight 2 SD statistical thresholds early in 2021 (+6.40%) and remained consistently elevated through 2024 (+8.90%). For females of the same age bracket, the elevation only cleared the 2 SD statistical significance line during the major peak of 2022 (+9.20%).
- Extreme Longevity Surge in Females (95+): Because females make up the large majority of the population surviving past age 95, viral entry into aged care facilities during 2022 resulted in an immense relative surge of +34.20% above historical baselines for women in this bracket—compared to +26.80% for men.
- Young Adult Divergence (25–44): Young men in the 25–44 category saw statistically significant spikes across four consecutive years (2021–2024), driven partly by delayed healthcare access alongside shifts in external acute injury and cardiovascular baselines. Women in the same group remained within expected baseline limits for a wider portion of the pandemic layout.
BIRTH DATA
Australia does not do records on miscarriages, so it's difficult to get a picture of what is happening with births, other than for the years 2023, 2024 the number of births fell far below normal range.
Year |
Actual Registered Births |
Difference
from Baseline Mean |
Percentage
Deviation |
Statistical
Status |
|---|---|---|---|---|
2020 |
294,369 |
-14,456 |
-4.68% |
🛑 Below Range (Significant Deficit) |
2021 |
309,996 |
+1,171 |
+0.38% |
Within Normal Range |
2022 |
300,684 |
-8,141 |
-2.64% |
Within Normal Range |
2023 |
286,998 |
-21,827 |
-7.07% |
🛑 Far Below Range (Extreme Anomaly) |
2024 |
292,318 |
-16,507 |
-5.35% |
🛑 Below Range (Significant Deficit) |
Key Analytical Takeaways
- The 2023 Birth Slump: The year 2023 represents the most extreme statistical anomaly of the decade, crashing more than 4.6 Standard Deviations below the baseline mean
AIHW Clinical Stillbirth Deviations Against Historical Baseline (2020–2024)
All absolute figures are rounded to the nearest whole integer. Percentages are rounded to two decimal places.
Year |
Actual
Clinical Stillbirths |
Difference
from Baseline Mean |
Percentage
Deviation |
Statistical
Status |
|---|---|---|---|---|
2020 |
2,273 |
+43 |
+1.91% |
Within Normal Range |
2021 |
2,278 |
+48 |
+2.13% |
Within Normal Range |
2022 |
2,380 |
+150 |
+6.71% |
Within Normal Range (Elevated Upper Tier) |
2023 |
2,525 |
+295 |
+13.21% |
🛑 Above Range (Significant Excess) |
2024 |
2,540 |
+310 |
+13.88% |
🛑 Above Range (Significant Excess) |
The data suggests that Australians are having fewer children and more still births. I personally know of 3 young couples that had still born babies from the period of 2020-2026, and this is very concerning that based on probability theory, I would have expected more still births recorded. In the past I rarely heard about a still birth but to now know of three couples within my immediate network is very troubling.
Lastly, I thought it would be interesting to see what people were dying of.
| Broad ICD-10 Chapter Category | 2023 Deaths | 2024 Deaths | % of 2024 Total |
|---|---|---|---|
| Neoplasms (All Cancers combined) | 51,215 | 52,431 | 28.0% |
| Diseases of the Circulatory System (Heart, Stroke, Vascular) | 41,830 | 42,126 | 22.5% |
| Diseases of the Nervous System & Mental/Behavioural (Inc. Dementia) | 26,450 | 27,104 | 14.5% |
| Diseases of the Respiratory System (Flu, Pneumonia, COPD) | 16,311 | 18,352 | 9.8% |
| External Causes of Mortality (Accidents, Falls, Suicides, Overdoses) | 14,112 | 14,561 | 7.8% |
| Diseases of the Digestive System (Liver Cirrhosis, Gastrointestinal) | 7,125 | 7,288 | 3.9% |
| Endocrine, Nutritional & Metabolic Diseases (Inc. Diabetes) | 7,015 | 7,154 | 3.8% |
| Diseases of the Genitourinary System (Renal/Kidney failure) | 5,230 | 5,410 | 2.9% |
| Certain Infectious & Parasitic Diseases (Inc. Sepsis, COVID-19) | 6,510 | 5,122 | 2.7% |
| All Other Chapters Combined (Congenital, Skin, Musculoskeletal, etc.) | 7,333 | 7,720 | 4.1% |
| Sovereign National Total | 183,131 | 187,268 | 100.0% |
| External Cause Sub-Category (ICD-10) | 2023 Deaths | 2024 Deaths | % of 2024 External Total |
|---|---|---|---|
| Accidental Falls (W00–W19, X59.0) | 4,990 | 5,197 | 35.7% |
| Intentional Self-Harm / Suicide (X60–X84, Y87.0) | 3,214 | 3,326 | 22.8% |
| Other Unintentional Accidents (Transport, Overdoses, Drownings) | 5,638 | 5,765 | 39.6% |
| Assaults / Homicides (X85–Y09) & Undetermined Intent | 270 | 273 | 1.9% |
| Total External Causes Chapter Total | 14,112 | 14,561 | 100.0% |
CONCLUSION
There is so much more to write and talk about but at this point with all this talk of preparing for internet outages, war, extreme weather events, cyber attacks, pandemics, etc..the data from Australia is saying that there is continued and sustained excess deaths, meaning that people are dying younger than they used to and we are seeing the effects of the biological weapon in the population especially those who have underlying health conditions or who are elderly.
The population is immuno-compromised now due to COVID-19 meaning other stresses whether that is infection, poor nutrition, stress, lack of sleep or sunshine, dehydration, over-exercising, extreme heat or cold, mould, radiation, etc.. will lead to increases in disease and deaths.
We will see what I described as the Hunger Games unfold.
The Digital Duty of Care Bill has passed the lower house and while most articles are public, I am giving fair notice that I will be putting controversial content behind a paid paywall because I will not be a martyr for a world that just doesn't care but for those who want to receive my insights, I will continue to write until I guess the lights go out completely.
I fully expect due to the latest exploits found by AI in php, hacking, online fraud and the way compliance is being done for domains, that the internet will become more regulated.
SUPPORT
Thank you to those who have supported this website via paid subscription or donation or through my business. If you enjoy my articles and posts, do consider contributing in some way. Life is energy. The grass grows where it is watered. Alternatively support links below for products and services that support me directly.
I have made this article public for now and you are free to do your own analysis. I am not employed as a Statistician and it is a shame that for all the education in this country, no one else has done similar and we are now simply accepting elevated deaths and disease as the "new" normal.
I don't expect anything to change politically. Writing this article for me has been important to cut through the noise with data and AI has been very helpful to do the analysis when told where to find the data rather than just regurgitating what the ABS or other official sources have spewed out and while people might suggest that AI is hallucinating, I have basically instructed it to do the calculations and it has returned the results with the benefit of having a degree in Statistics.
Do with them what you will but as it has always been my motivation that I can inspire people to live better, healthier and more connected lives and the data is confirming what I have previously shared and we will continue to see more deaths which will be covered up by things like war, food shortages, energy outages, etc.. and no government in the world has ever acknowledged bio-warfare waged against humanity, which tells you everything you need to know.
I am not someone that is doom and gloom but the solutions I have also written and spoken about. Faith, hope and love. These are so important, especially in these dark times.
 Jeanee Rose Andrewartha

Uncensored Wisdom Paid Subscription is $5 a month or $50 a year (in Australian dollars). Cancel at any time. The Gifting page accepts once off donations in USD.
You can also support my family in the links below:
Passion Computing
If you want to work with me on a website or media related project, do get in touch. We do everything from custom websites to managing domains, email, hosting, graphic design, programming, copy writing, consulting, video editing, and photography.
My business Passion Computing, that we are one of the very few website development businesses that can offer in-house programming and design, and we don’t bill until after the project is completed and the final product finished and signed off on. Fixed price quote generally unless the client has very unusual requirements. We also offer a full suite of web and domain related services - see below. Small jobs and referrals welcome.
Share our business details to others.



Colostrum supports gut integrity, signalling and absorption and when the gut works, the body responds. A stressed gut blocks metabolic process and colostrum works systemically, at the same time restoring the internal environment, restoring balance and providing the conditions for the body to heal. It is a baby's first food and bovine colostrum acts in a similar way, preparing the gut for digestion.
Anovite Colostrum is a food - raw, organic and from small family farms. Link to purchase below or become an associate. Be the change.

About Me
 Jeanee Rose Andrewartha

https://www.linkedin.com/in/jeanee-rose-andrewartha-42417b252
https://www.linkedin.com/company/passion-computing/
